
NTEP (National TB Elimination Program, 2021)
Epidemiology of Communicable DiseasesHealth Programmes in India
1. NTP: National Tuberculosis Control Program, 1962
- Reviewed in 1992: NTP had not achieved its aims or targets
2. RNTCP: Revised National Tuberculosis Control Program, 1992
- Incorporating ‘Directly Observed Treatment Short-course’ (DOTS) strategy
Stop TB Strategy, 2006
Announced in 2006 by WHO and adopted by RNTCP
- Continue and expand DOTS
- Addressing TB/HIV
- Addressing MDR-TB
- Health system strengthening
- Engaging pvt and alternative practitioners
- Empowering patients
- Promoting research
- Diagnostics
- Treatment
- Vaccine
- National Airborne Infection Control Guidelines
- Practical Approach to Lung Health
End TB Strategy, 2014
- Approved by WHO in 2014, as TB was still the deadliest infectious disease globally
- A 20 year program
- Vision: Zero death, disease and suffering due to TB
- Interventions are both:
- Health related and
- Social (as TB is associated with social factors esp. poverty)
- End-TB Strategy includes
- Patient centered care and prevention
- Bold policies & patient support
- Intensified research and innovation
3. NTEP: The program has been renamed as 'National Tuberculosis Elimination Program in 2020
- GOI (MoHFW )has committed to end TB by 2025,
- 5 years ahead of the global target under Sustainable Development Goals
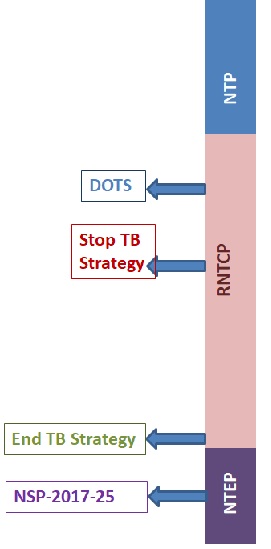
National Strategic Plan 2017-25 (NSP) has been made for Tuberculosis Elimination by 2025
- Major organizational change: creation of a sub-district administrative level i.e. at the Block/ PHC level
- The ‘Tuberculosis Unit’ (TU)
- MO-TC has the overall responsibility of management of TB Control Program at the TU
- The team of STS and STLS are under the administrative supervision of the MO-TC and the DTO
PHI is a health facility, having at least 1 medical officer.
- Dispensaries, PHCs, CHCs, referral hospitals, major hospitals, specialty clinics or hospitals, TB hospitals, ART Centres and Medical colleges in the district.
- Even the private and NGO participating in NTEP are considered as PHIs
- Some of these PHIs also function as DMCs.
- PHI has the main responsibility of case finding & management.
- If > 1 MO is posted in a PHI, one is to be identified for the responsibilities of the NTEP.
- Referral for screening for DM is the responsibility of the PHI where TB Rx is initiated
- All Diabetic TB patients should be linked for diabetic care.
TB Laboratory Services: 3-tier system
- The peripheral laboratories
- State level- Intermediate reference laboratory (IRL),
- Central level
For details, click here
Supporting Facilities for NTEP
NTEP: Key activities include
1. Active TB case finding
2. Newer and shorter regimen
3. Private sector engagement
4. Financial/nutritional support to TB patients
5. IT enabled
- surveillance,
- preventive and
- awareness measures
Active Case Finding (ACF)
Active case finding, as opposed to passive case finding, means:
Going out and identifying TB in individuals who don’t come themselves for health care using community volunteers with proper training and supervision
- ACF is to be done in among high-risk groups (HRGs) Which have been identified as:
- PLHIV (people living with HIV)
- All contacts of bacteriologically confirmed pulmonary TB patient
- Other risk groups (silicosis, immuno-compromised, organ transplant, hemodialysis, anti TNF-therapy, etc).
- Migrants
- People living in
- urban slums,
- construction sites, and
- hard-to-reach areas
- It’s planned to conduct 3 rounds of ACF/year
- TB patients detected during ACF are referred for Dx and TB Rx
- Patients with other morbidities
TB Comorbidities
(Detecting TB in patients with other Morbidities)
TB and HIV
- HIV Testing for TB Patients (including Presumptive TB cases)
- Screening for TB among HIV patients (Intensive Case Finding /ICF)
- using 4 symptom complex
- Cough of any duration,
- Fever,
- Weight loss,
- Night sweat
- ICF is to be done at ICTC, ART center and Link ART Centers
- ICF is also to be done even among HIV high risk groups (HRG)
- Isoniazid preventive treatment (IPT) for all people living with HIV (PLHIV)
- TB pt. with HIV: same daily treatment for same duration as HIV-negative TB pts.
TB and Diabetes
- Screening of TB patients for Diabetes
- If DM found, then linkage to DM care center
- Screening of Diabetes patients for TB (4 symptom complex/every visit)
- If found to have TB, linkage with TB management center
Newer & Shorter Regimens
For details, click here
Patient support for TB Elimination
- Treatment Support
- Adherence support strategy
- Nutritional Support
- Mitigating catastrophic expenditure (such as those provided through DBT)
- Airborne infection control in Community and Facility
- Patient help desk and grievance redressal.
Treatment & Adherence Support
- To Minimize delay in starting treatment
- Maximize adherence by
- Monitoring & reporting dose administration
- Support for preventing treatment interruption
A support plan is developed right at time of diagnosis, in consultation with the patient and the relevant health staff.
This plan should include:
- A home visit for counseling of the patient and family members

- Follow-up schedule at PHI and for lab investigations
- Linkages for co-morbidity management
- including assessment of nutritional status and nutrition support
- Adherence support using tools like
- 99DOTS,

- Retrieval of treatment interrupters,
- Screening for adverse reactions,
- Supervision of treatment supporter etc.
Nutritional support
- All individuals with active TB receive
(i) An assessment of their nutritional status and
(ii) Counseling based on their nutritional status
- At diagnosis and throughout their treatment.
(iii) Any malnutrition detected, is managed as per WHO recommendations.
- NTEP guidelines for nutritional assessment and counseling of TB patients are in the Document
- Nutritional Care & Support for TB patients in India
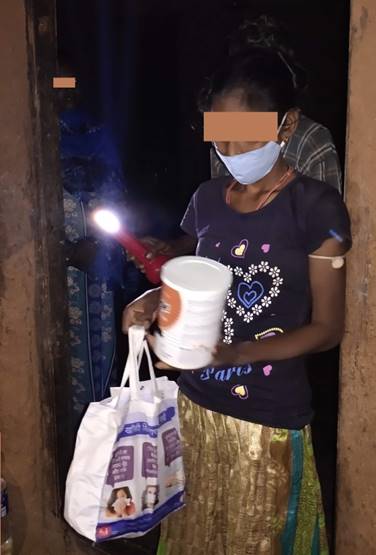
Nikshay Poshan Yojana (NPY)
- DBT at notification and then during treatment
(DBT=Direct Benefit Transfer i.e. money credited directly to the beneficiary’s account)
- Rs. 500 each month of treatment and
- Up to Rs. 1000 as an advance.
Mitigating catastrophic expenditure
- Catastrophic expenditure: Includes expenses for tests, medicines, travel, loss of wages etc.
- An END TB Goal is: reducing catastrophic expenditure
- Free diagnostic and treatment for the private sector too
- Financial support to patients and care providers (DBT)
a. Nutritional Support (Rs.500/-month)
b. Travel support to Tribal Patients (Rs750/-)
c. Private Practitioners incentives (Rs.500/- for Notification & Rs.500/- for reporting of Treatment Outcome )
d. Treatment supporters Honorarium (Rs.1000/- to Rs.5000/-)
Support for airborne infection control
- TB patients are educated on prevention of airborne infection
- At home and at work place.
- E.g. cough hygiene
- Airborne infection control measures are implemented in Health Facilities, Community, and at household level.
- Health facilities
- Increased ventilation,

- Reduced crowding,
- Faster processing of patients’ and samples (fast tracking),
- Wet mopping
- Cough etiquette
- Increased ventilation,
- Patients are provided with
- Spittoon
- Disinfectant and
- Reusable masks and educated on their use.

- During house visits, the health workers observe for cough hygiene and reinforce AIC information.
- Details can be found the ‘Guidelines for Airborne infection control’.
Patient Grievance Redressal
- Patients can provide feedback and report grievances to the DTO on
- Paper or email or
- Through the National Call Centre (Nikshay – Sampark).
- If the request/grievance is not addressed at a particular level it will be escalated to the next higher level.
- At all points, the patient should be informed of the status of his/her submission
Supporting TB Patients under Private Providers
- TB control officers mustn’t attempt to divert patients from private providers to the public system
- Regulatory measures must also be used judiciously.
- The approach includes:
- Engagement of providers
- Linkage of services
- Patient support/ Public health actions
- Regulatory Measures
- Process of engagement of PPs
- 1. Engagement of providers
- Mapping of private providers-
- Allopathy and AYUSH
- Chemists
- Laboratories
- NGO, corporate sector, health facilities under other Ministries, Public Sector Enterprises etc.
2. Prioritization of providers by DTO
- Following is considered for prioritization
- allopathic practice
- Patient load (Respiratory or TB patient load)
- AYUSH providers
- Pharmacies and their TB prescription load.
- Diagnostic laboratories with TB diagnostic services and their test load
3. Collaborate with Private Providers
- All providers should be registered in NIKSHAY
- DTO can involve an NGO/agency to reach out to private providers.
- The private providers are sensitized through
- Clinic visits, peer pressure or professional associations
- Scientific and clinical information about TB management
- Then an onboarding kit is provided to the doctor
- Notification formats
- List of diagnostic/treatment services free & paid
- E.g. free X-ray, smear microscopy, CBNAAT, TrueNat etc.
- Free anti-TB drugs
- Sputum collection containers/falcon tubes


Regulatory measures - GOI has made notification of TB cases mandatory on 7th May 2012.
- Legal backing for not notifying a TB patient.
- punitive measures as per IPC 269 & IPC 270.
- Use clinical establishment act (CEA) wherever it is being implemented.
- This will help to identify providers who are registered under the CEA and not registered with NIKSHAY
Involvement of Medical colleges in NTEP
- Facilities like
- DMC/CBNAAT lab,
- Treatment centre,
- Drug resistant TB centre etc. in Medical Colleges.
- It also facilitates research pertaining to TB in Medical colleges.
- Core Committees in medical colleges for inter-departmental coordination
- Operational research is one of the important activities of Medical Colleges.
Treatment of Pediatric TB
- For pediatric patients, formulations with daily dosages as per 6 weight band categories are made available
- All adolescents up to 18 years of age and weighing less than 39 kg, are to be treated using pediatric weight bands and
- Children weighing more than 39 kg with adult weight bands
IPT (isoniazid preventive treatment) in children:
- Preventive chemotherapy with isoniazid (H)
- All children ≤ 5 years who are in contact with all forms of Drug sensitive TB case.
- They are examined and investigated to rule out active TB
- If found to have TB, they are treated appropriately
- If active TB is ruled out, IPT given
- IPT dosage: INH 10 mg/kg body weight daily for 6 months.
TB in the Private Sector
- Standards for TB care in India: Guidelines made available for treatment & follow-up of TB patients
- Mandatory TB notification
- NIKSHAY: a web enabled application to facilitate monitoring of universal access to TB patients data by all concerned
- Ban on Sero-diagnostics and
- Regulatory tools are limited.
National Strategic Plan 2017-25
NSP has 4 pillars of strategy
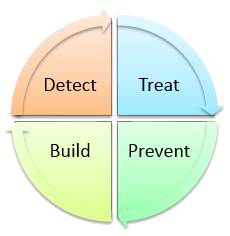
- Detect: all drug sensitive cases (DS-TB) and drug resistant TB cases (DRTB) esp. from pvt providers and undiagnosed TB cases in high-risk groups (prisoners, migrant workers, PLHIV/AIDS, contacts etc.).
- And report these
- Treat: Provision of free TB drugs in the form of daily fixed dose combinations (FDCs) for all TB cases is advised with the support of directly observed treatment (DOT).
- Screening of all patients for rifampicin resistance
- Prevent
- Air-borne infection control measures at health care facilities
- Treatment for latent TB infection in contacts of bacteriologically-confirmed cases
- IPT
- BCG
- Address social determinants of TB through intersectoral approach.
- Build: Health system strengthening for TB control
- enabling policies, empowering institutions and human resources
References
- Park’s Textbook of Preventive & Social Medicine, 26th ed. 2021. Bhanot Publishers, Jabalpur, M.P., India
- TRAINING MODULES (1-4) FOR PROGRAMME MANAGERS AND MEDICAL OFFICERS; New Delhi, India: Central TB Division, MoHFW, Government of India; July 2020., Available from:www.tbcindia.gov.in
- Prathiksha G, Daniel BD, Natrajan M. Active case-finding for tuberculosis in India. Natl Med J India 2019;32:90-95