
Control of Diphtheria
Control of Diphtheria
- Treatment of
- Cases and
- Carriers
- Management of the ‘Contacts’ and
- At the community level
- Increasing coverage of immunization with diphtheria toxoid
Treatment of Cases and Carriers
Early detection
- An active search for cases and carriers should start immediately amongst family and school contacts
- Carriers can be detected ONLY by culture
- Swabs should be taken from both the nose and throat
- Examined by culture for diphtheria bacilli
- Tests should also be done for virulence of the organism
Isolation
- All cases
- Suspected cases and
- Carriers should be
- Promptly isolated
- Preferably in a hospital
- For at least 14 days or
- Until proved free of infection
- At least 2 consecutive
- nose and throat swabs,
- taken 24 hours apart
- should be negative before terminating isolation
Treatment of cases and carriers
- Cases:
- Diphtheria antitoxin should be given without delay,
- IM or IV, Dose ranges from 20,000 to 1,00.000 units depending up on the severity
- Mild early pharyngeal or laryngeal disease: 20 to 40,000 units
- Moderate nasopharyngeal disease : 40 to 60, 000 units
- For severe, extensive or late (≥3 days): 80 to 1,00,000 units
- Penicillin or erythromycin for 5 – 6 days to clear the throat of C. diphtheriae and thereby decrease toxin production
- The case should be reported to the health authorities Immediately
- Once recovered, active immunization with diphtheria toxoid should be provided
- Carriers:
- Treat with 10 days course of oral erythromycin
Management of Contacts
Contacts merit special attention
- They should be throat swabbed
- Determine the immunization status and take further action accordingly (shown below)
- Contacts need to be placed under medical surveillance
- Examined daily for evidence of diphtheria for one week
- Bacteriological surveillance weekly for several weeks (weekly swabbing)
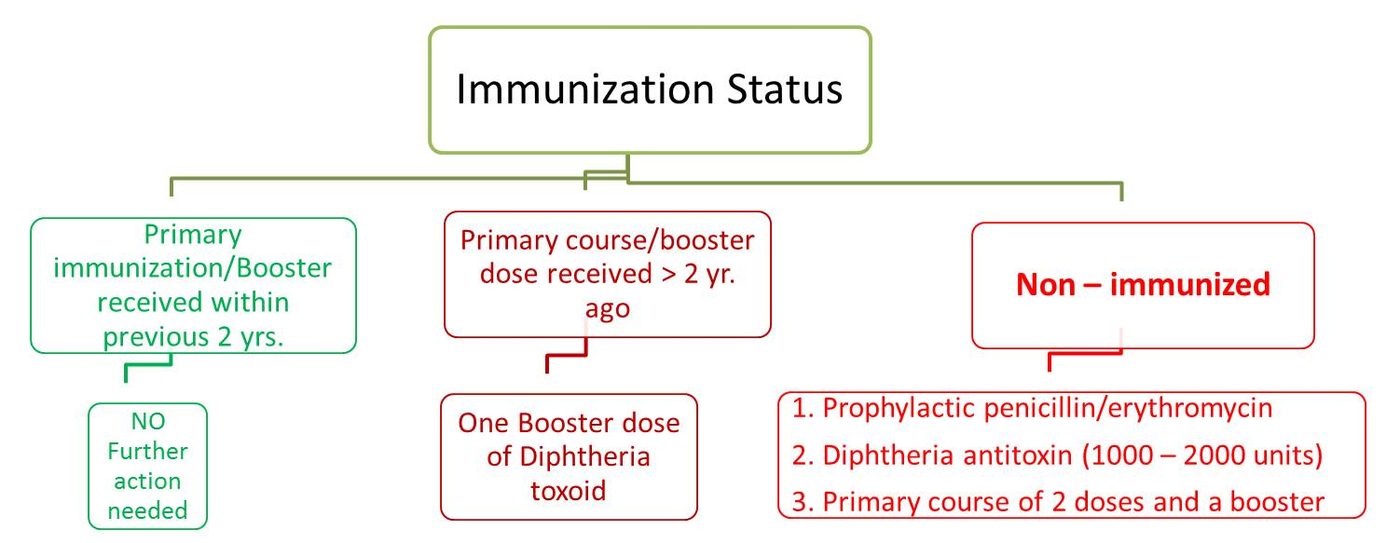
Control in the Community
- The only effective control is by active immunization
- With diphtheria toxoid
- Of all infants
- As early in life as possible
- Subsequent booster doses every 10 years thereafter
- The aim is to immunize before the infant loses the maternally derived immunity
- So that there is continuous protection from birth without any gap in immunity to natural disease
- Immunization does not prevent the carrier state
- As the vaccine being a toxoid is not directed against the organisms
- Hence non immune individuals are not protected by a high level of population coverage
- This implies that immunization must be maintained at high level
Diphtheria Immunization
The toxoid vaccine is available in different forms as mentioned below:-
- Combined/mixed vaccines
- DPT (Diphtheria, Pertussis, Tetanus) vaccine
- Pentavalent vaccine (Diphtheria, Pertussis, Tetanus, Hepatitis B and Hib)
- DTaP (Diphtheria, acellular Pertussis, Tetanus) vaccine
- DT (Diphtheria, Tetanus toxoid) vaccine
- dT (Diphtheria, Tetanus -adult type) vaccine
- DTaP, IPV, HepB (Diphtheria, acellular Pertussis, Tetanus with hepatitis B and Polio)
- Paediatric formulations (DT, DPT and DTaP) contain a similar amount of tetanus toxoid as adult Td, but contain 3-4 times as much diphtheria toxoid.
- Single vaccines
- FT (Formal toxoid)
- APT (Alum precipitated toxoid)
- PTAP (Purified toxoid aluminium phosphate)
- PTAH (Purified toxoid aluminium hydroxide)
Immunization Schedule for Diphtheria
For routine immunization of infants:
- Combined vaccines are preferred
- Simultaneous immunization against more than one disease
- The pertussis component enhances the potency of diphtheria toxoid
- Optimum age: as early as 6 weeks
- Young infants respond well even in presence of low to moderate levels of maternal antibodies
- Number of doses
- Three doses of DPT/ Pentavalent vaccine/ DTaP+ IPV+ HepB
- 4 weeks apart (6, 10, & 14 weeks of age as per NIS)
- for primary immunization
- Booster at least 6 months later and AFTER 12 months of age (16 – 24 months as per National Immunization Schedule or NIS)
- Second booster (DT only) at 5 – 6 yr.
- Dosage – 0.5 ml
- Route of administration – deep intramuscular (IM)
- Site of administration – Lateral aspect of thigh for infants
For older children: After 5 yr of age –
- Only 2 doses of DT,
- 4 weeks apart,
- Booster 6 months – 1 yr, later
For children > 12 yr. old and Adults
- Preparation of choice is dT
- This is the adult type of diphtheria tetanus vaccine
- It contains much lesser amount of diphtheria toxoid but same amount of TT as pediatric preparation
Antisera
- Diphtheria antitoxin, prepared in horse serum
- Is still the mainstay of passive prophylaxis and treatment of diphtheria
- It has been shown that protection against diphtheria toxin is a quantitative phenomenon
- A serum antitoxin titer against a small dose of toxin may not protect against a larger dose
- Failure of diphtheria immunization may occur due to this phenomenon
References
- DIPHTHERIA - A RE-EMERGING THREAT. CD Alert, Jan – Mar 2008; 12 (1): 1-8 available on http://www.ncdc.gov.in/writereaddata/linkimages/Jan-March%20087398246488... downloaded on 16 Dec 2016
- Communicable Disease Management Protocol – Diphtheria. August 2016. available at: http://www.gov.mb.ca/health/publichealth/cdc/protocol/diphtheria.pdf downloaded on 16 Dec 2016
- http://www.immunize.org/catg.d/p4203.pdf accessed on 16 Dec 2016
- Park’s Textbook of Preventive and Social Medicine, 23rd Edition, Diphtheria, 161-163
Control of diphtheria: Control of Diphtheria
Management of Contacts of a Case of Diphtheria: Management of Contacts of a Diphtheria Case
Diphtheria – Epidemiology, Clinical Features & Management: Diphtheria – Epidemiology, Clinical Features & Management